Aug 10, 2024 Prof G Conversations Niall Ferguson, a historian, author, senior fellow at the Hoover Institution, and columnist at The Free Press, joins Scott to discuss why we’re currently in Cold War II, his thoughts on the US presidential candidates, and gives us an update on conflicts happening around the world. Follow Niall, @nfergus
Media outlets affiliated with the Axis of Resistance published a video titled "Inevitable Revenge" in anticipation of the retaliatory operation to the Israeli escalations in the region. pic.twitter.com/7abGZc8NDF
If you’re experiencing memory issues after a head injury, you are not alone.
Some degree of memory loss after a head injury is common. For most, memory loss (and other symptoms) will resolve within a few days or weeks, but a few patients will continue to experience problems for months or even years after their injury. This ongoing condition is called post-concussion syndrome (PCS).
Many PCS patients end up frustrated because traditional treatment approaches do not address the underlying causes of their memory issues. Common medical advice is geared to help patients cope with their memory impairments rather than to recover brain function.
At Cognitive FX, we take a different approach. We target the underlying causes of symptoms that linger after a head injury. Our methods are based on cutting-edge diagnostics, recent scientific research, and an unprecedented, multidisciplinary collaboration that brings the best available therapies together under one roof.
This rigor is why Cognitive FX was the first treatment provider able to help Riley Horner, a young girl whose memory reset every few hours to June 11, 2019.
Key to our approach is treating the brain as an interconnected whole rather than trying to treat one symptom at a time. To “fix” your memory means all parts of the brain that contribute to memory formation and recall need to work well. Our patients often come in with deficits in memory, attention, and sensory processing that need to be rehabilitated simultaneously for them to see marked improvement.
Later in this post, we’ll detail this treatment approach and give examples of patients who recovered significantly from their memory loss symptoms. Throughout, we’ll cover needed information such as…
If you’re experiencing symptoms that won’t resolve after a mild traumatic brain injury, you’re not alone. And you’re not crazy. 90% of our patients show symptom improvement after just one week of treatment at our center specializing in post-concussion therapy. To see if you are eligible for treatment, sign up for a consultation.
Types of Memory Loss You Could Experience After a Head Injury
Memory is not just one skill. There are several kinds of memory, including short-term memory, long-term memory, working memory, and episodic memory. Concussions (mild TBI, or mTBI) and other head injuries can affect different types of memory, potentially causing different types of amnesia.
Anterograde Amnesia
Anterograde amnesia is the most common type of memory loss after a concussion. It’s often accompanied by other cognitive problems, such as difficulties with attention.
Patients with this type of memory loss struggle to remember new information but can remember events from before their injury.Anterograde amnesia leaves patients with difficulties at school or work and interferes with their ability to carry out their daily tasks. This type of short-term memory is frequently the last cognitive function to return as the patient recovers.
Difficulty remembering conversations or events just minutes after they occur
Difficulty remembering the names and faces of people they’ve just met
Difficulty remembering the storyline in movies recently watched or books recently read
Confusion about current events, dates, and times. Patients often lose track of time or feel unsure about the date
Difficulty retracing a route they took earlier in the day
Patients may remain confused and unable to store new memories for days, weeks, or even months after their injury. One extreme case of post-traumatic amnesia is that of teenager Riley Horner. In 2019, Riley was at a dance in Springfield, Illinois, when she was accidentally kicked in the head.
At the hospital, doctors ran a few tests and couldn’t find anything wrong, so Riley went home. However, the 16-year-old woke up the next day with no recollection of her injury and still thinking she was going to the dance that evening. In the days that followed, her memory started resetting every two hours. For six months, not only was she unable to make new memories, but she constantly woke up thinking it was the 11th of June, the day of her injury.
Medical professionals struggled for months to explain the extent of Riley’s condition. MRI and CT scans on Riley’s brain showed no abnormalities, and sadly, doctors were unable to suggest any potential treatment. This is not surprising given that structural CT and MRI scans cannot show the functional damage caused by concussion.
After Riley’s story went viral, her family found Cognitive FX. After just one week of treatment with us, Riley started making her first memories. By the end of week two, she was able to remember almost everything. “It’s truly a miracle, I don’t know what else to say! I have seen stuff here and there, but last night it was real to me that I have my daughter back! She will have a future,” said Sarah Horner, Riley’s mom.
While Riley did not regain 100% of her former cognitive ability, she was able to go back to school and pursue a college degree, a dream she had begun to worry wouldn’t happen.
Prospective Memory
Concussions may also affect prospective memory, in which patients can’t remember plans or other commitments long enough to attend them. Prospective memory is essential not just for daily living, but also for remembering activities important to recovery, such as taking necessary medications, completing rehabilitation exercises, and maintaining supportive social relationships.
Patients with loss of prospective memory may:
Forget to keep appointments or show up at the wrong time or day
Tell friends that they will visit at a certain time, then forget to do so
Forget important occasions, such as birthdays, holidays, and family events
Forget to take medicines at the right time
Forget to pick up children from school at a certain time
Forget to attend important meetings at work
Retrograde Amnesia
Retrograde amnesia is less common, but it can happen. Typically, patients lose the ability to recall events that have occurred during the period immediately preceding the brain injury. They may also be unable to remember events from days, weeks, or even years before the concussion. This is more common after a severe head injury.
Patients with retrograde amnesia may experience:
Difficulty remembering events that occurred before the concussion
Difficulty remembering general knowledge facts
Difficulty remembering names, faces, places, and dates that were familiar before the injury
Inability to recall skills and abilities that they knew before the injury
Difficulty studying for exams at school
Inability to recall long-term memories that occurred during childhood
Sometimes patients struggle with both anterograde and retrograde amnesia. This is what happened to one of our patients, Ryan. His life was turned upside down after a car accident, causing a whole range of cognitive issues, including extensive problems with memory and focus.
When Ryan’s aunt told him about Cognitive FX, he decided to pursue treatment at the clinic. “Even after the first day, my energy level was already starting to go up. I was able to sleep better at night, and as the week went on, my energy — I have a ton of energy now. My focus is a lot better. I can multitask again, my long-term memory is pretty good now too, and short-term is not a problem. I can remember things people tell me, things I see.”
“The people you work with — they’re so friendly,” he added. “It’s the only place I’ve gone to where everyone really cares and asks you every day how you’re doing. It’s like a family environment, which helps you become more comfortable, which is important when you’re trying to do therapy.”
Memory of the Injury
Sometimes, patients with PCS don’t remember the injury itself. In simple terms, this means the brain has not stored the injury as a memory.
If you can’t remember the events that led to your concussion, you likely never will. Your brain didn’t store those memories. If that’s the case with you, the best way to learn about the injury is to ask family members, friends, or medical personnel who may have relevant information.
Dissociative Amnesia
Though extremely rare, this type of memory loss can cause patients to forget not only their memories but also their identity. In extreme cases of this disorientation, they may not even recognize their own reflection in the mirror. This most often occurs after severe traumatic events, but in most cases, patients begin to remember themselves as they recover from the severe TBI.
Causes of Memory Loss After a Head Injury
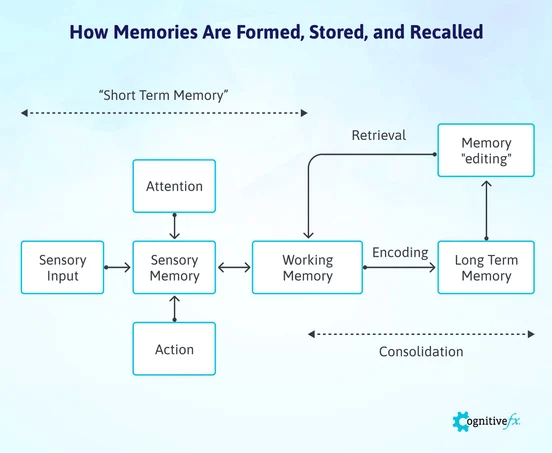
Before we discuss how PCS patients can experience memory problems, it helps to understand how memory works. In very simple terms, there are three steps to learn and memorize new information: encoding, storage, and retrieval. Encoding is the initial learning of information; storage refers to maintaining information over time; and retrieval refers to the ability to access information at a later stage. If you want to find out more, we’ve written in more detail about how memory works in a healthy brain in our post about post-COVID memory loss.
Forming and recalling a memory requires many parts of the brain to work in harmony. Concussions disrupt this process, but it’s impossible to determine exactly which step is affected. One reason for this is that these three steps are not as separate as this description implies. Rather, all three steps are interconnected. For example, how we encode a new memory will determine how it’s stored and how it can be recalled later. Patients also need to pay enough attention to form a new memory in the first place, and all the parts of the brain that encode, store, and retrieve memories need to be in full working order.
Post-traumatic memory loss is likely due to some combination of the following causes:
Structural Damage to the Brain
Several areas in the brain are involved in encoding and storing memories, and damage to any of these areas can cause memory loss. Some of the main areas of the brain involved in memory include the:
Frontal cortex
Hippocampus
Hypothalamus
Amygdala
As different types of memories use different areas and different systems in the brain, concussions can cause memory loss in one type of memory but leave other types intact. For example, damage to the frontal cortex is more likely to cause short-term memory loss, whereas damage to the hippocampus disrupts the memory consolidation process used to store long-term memories.
Autonomic Nervous System (ANS) Dysfunction
The autonomic nervous system (ANS) controls a variety of bodily functions, including blood pressure, heart rate, and breathing patterns.
Most of this control is achieved via the sympathetic (SNS) and the parasympathetic (PNS) nervous system. The SNS prepares your body to react to a threat (known as the “fight or flight” reaction), and the PNS helps to calm the body (known as the “rest and digest” part of the nervous system). Under normal circumstances, the PNS and SNS work together in harmony and change dominance when needed.
Concussions, however, can disrupt this balance, and the SNS tends to stay activated even when it’s not needed. This causes a variety of physical symptoms, such as headaches, blood pressure changes, heart palpitations, and problems breathing, to name just a few.
In addition to regulating physical body functions, recent studies have identified that the PNS also enhances memory skills when it’s active. Researchers don’t fully understand this mechanism, but there’s some speculation that an active PNS improves how new information is processed by regulating dopamine production in the brain. Patients with an underactive PNS may see memory improvement as their autonomic nervous system responds to therapy.
Problems with memory can also develop due to changes in neurovascular coupling. When brain cells need energy and oxygen to perform a particular task, they request these resources from surrounding blood vessels. These vessels then deliver the right resources to the right place at the right time in the right amount. This complex, dynamically regulated connection between the vascular system and the brain is called neurovascular coupling (NVC).
However, concussions disrupt this communication between brain cells and blood vessels. As a result, resources may be delivered to the wrong place, at the wrong time, or in the wrong amounts (too much or too little), which means the brain can’t continue to operate normally. Depending on which areas are affected, this disruption may cause different symptoms. For example, if it affects areas involved in creating new memories, patients may experience difficulties in processing and retrieving different types of memories.
Inflammatory Response
Concussions also trigger localized inflammation near the site of injury, affecting how these areas receive the resources to maintain normal operations. This can persist for months and cause symptoms such as headaches, dizziness, cognitive impairment, irritability, anxiety, and insomnia. High inflammation levels are also associated with poorer cognitive skills, including problems with short-term memory and learning new information.
Sleep Disturbances
Sleep is vital for the formation and consolidation of memories. Getting enough high-quality sleep helps with multiple cognitive skills, including attention, concentration, memory, problem-solving, creativity, emotional processing, and judgment.
Many PCS patients experience sleep disturbances, which in turn can cause memory issues. For example, broken sleep cycles impair memory consolidation. In addition, patients who are sleep-deprived can form false memories and have poorer working and visual-spatial memory.
The ANS is also involved in this process. When you focus your attention on something with the intention to form a new memory, your brain activates the sympathetic nervous system and increases breathing rates to promote blood flow to the brain. Under normal circumstances, this is a short-term change; the parasympathetic nervous system reduces breathing rates back to normal soon after. However, as described earlier, in PCS patients, the sympathetic branch is dominant most of the time. As a result, both increased sympathetic activity and decreased parasympathetic activity lead to poorer cognitive function, including memory and attention.
Common Treatment Approaches for Memory Loss in PCS Patients
Most treatment providers are unable to address the underlying cause of memory loss in mild head injury patients. There are some commonly offered, helpful therapies and options that we’ll discuss below. Then, we’ll explain how treatment at Cognitive FX takes the best of these treatments and improves upon them to get better results for PCS patients.
Cognitive Therapy
Cognitive therapy is designed to help patients who are experiencing cognitive issues after a concussion, such as poor memory, difficulties with attention, and problem-solving. A cognitive therapist will guide patients through exercises designed to improve those cognitive abilities.
Common exercises to help with memory may include:
Memorizing a list of words and recalling them later
Making up a story to connect different words to help with word recall
Naming as many items as possible for multiple categories, such as tools, animals, plants, countries, occupations, foods, sports, etc.
Occupational Therapy
Occupational therapy can be very beneficial for patients with memory loss. For example, therapists may ask patients to engage in concentration and memory games, such as word searches, card games, and puzzles.
Occupational therapists also work with patients to develop routines that minimize the impact of memory loss, creating compensatory strategies that allow patients to participate in many daily activities. For example, patients might write reminders and store important items, such as their car keys and phone, in the same place every day. Studies confirm these therapeutic interventions have a significant impact on memory, as well as mental health and overall wellness.
Psychotherapy
Memory problems may also stem from other conditions, such as depression and anxiety. The current theory is that anxiety and stress hinder memory skills because the brain diverts its attention and energy to identify the perceived threat instead of engaging in whatever cognitive task the patient is trying to complete.
Treating those conditions may help improve memory. In this case, talk therapies, such as cognitive behavioral therapy or counseling, are effective options. CBT encourages the patient to take an active role in managing their thoughts, feelings, and behaviors. It helps patients change how they think, feel, or act to improve their mood and reduce stress.
There is mounting evidence that mind-body therapies, such as meditation, mindfulness, and breathing exercises (which we teach our patients at Cognitive FX), are promising treatment options for memory problems.
For example, multiple studies show that engaging in regular meditation promotes beneficial changes in the brain, supports communication between different areas, and enhances nutrient utilization in regions involved in cognitive processing, memory consolidation, and attention. Ultimately, patients experience improved memory, attention, executive function, and processing speed to help combat the long-term effects of brain injury.
Music Therapy
Music exposure also positively affects the brain, helping combat loss of memory. Studies show that listening to familiar music improves cognitive processing, enhances communication between different areas of the brain, and stimulates activity in areas involved in emotion, working memory, and attention.
What’s more, music doesn’t just help patients retrieve stored memories, it also helps them create new ones. Healthy people scored better on tests of memory and reasoning after completing a course of moderate physical exercise to musical accompaniment (as contrasted to those who did not have music).
Medications
There are no medications specifically for the treatment of memory loss, but there are some prescription drugs, such as methylphenidate (Ritalin) and lisdexamfetamine dimesylate (Vyvanse), to assist with attention problems. This can sometimes help with memory. These medications often have side effects, and we advise that you discuss the pros and cons with your health care provider before starting any new medications.
You may come across many different dietary supplements that claim to help with memory problems. However, most of these, including apoaequorin, coenzyme Q10, omega-3 fatty acids, and various vitamins, lack compelling evidence to support their use. In addition, the U.S. Food and Drug Administration (FDA) does not test dietary supplements’ safety, effectiveness, or labeling before products go on the market. Our advice is to avoid using these products as memory enhancers, or at least, ask your doctor before you start taking anything.
Memory problems after a concussion or other head injury are rarely the only symptom a patient experiences. If you are experiencing memory loss or other ongoing memory symptoms, you’re likely also suffering from an assortment of other common concussion symptoms, such as emotional changes (sometimes mistaken for personality changes), headaches, dizziness, blurry vision, brain fog, and sleep problems.
These symptoms are best treated in combination instead of one by one. At Cognitive FX, we deploy multidisciplinary therapy and guided exercise to help your brain heal. This treatment process begins with an in-depth assessment to guide your therapy.
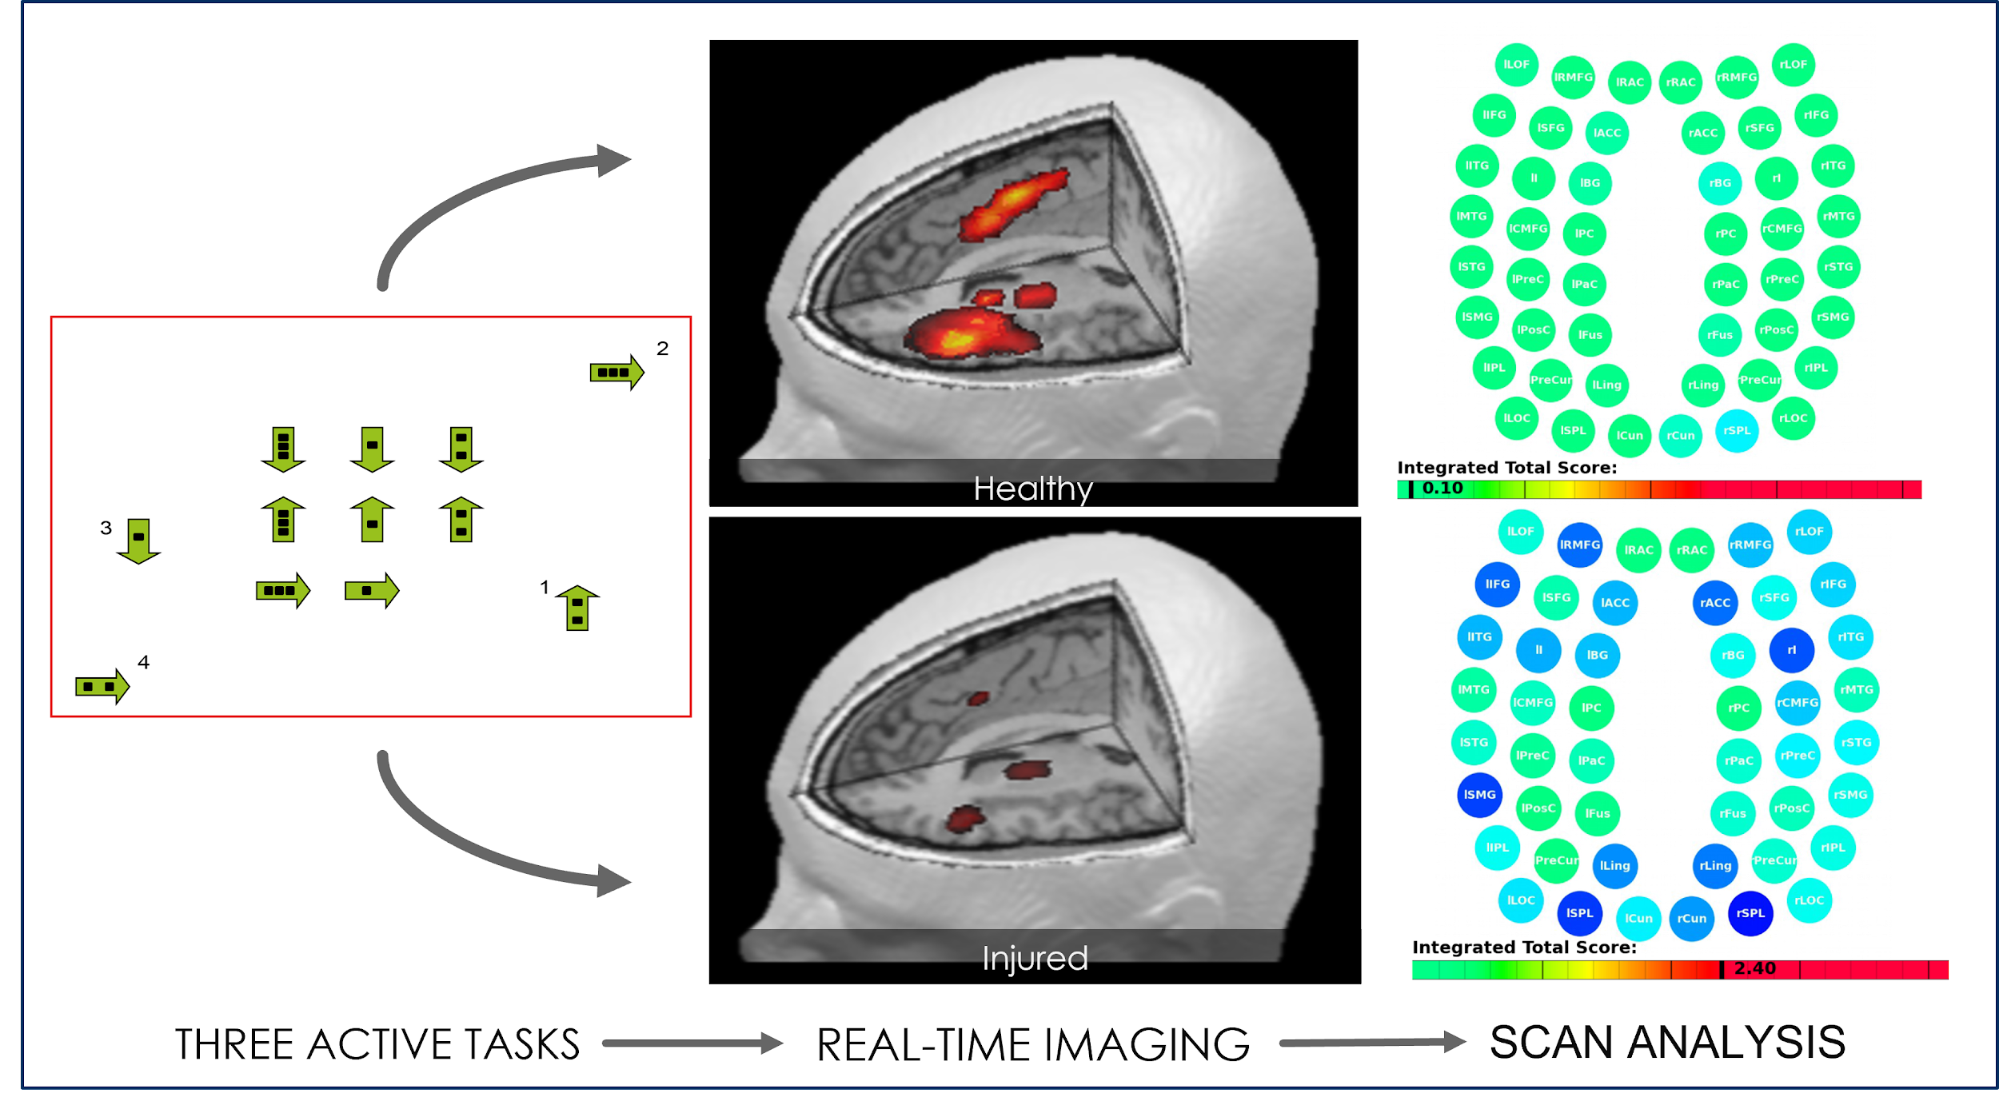
Key to our examination is a state-of-the-art brain imaging scan called functional Neurocognitive Imagining (fNCI). With this scan, our team can identify which areas of your brain were affected by the brain injury. In practical terms, the scan looks at 100 different areas in the brain while patients perform a series of cognitive tasks. It also looks at how these brain regions communicate with each other.
The results from the scan are then used to design a personalized treatment plan — called Enhanced Performance In Cognition, or EPIC. Here’s a snippet of a post-scan analysis of Dr. Alina Fong and Lauren Taylor Brem discussing how Lauren struggles to find words in moments of tension:
After you’ve discussed your results and treatment approach with our team, we begin a three-step process:
Prepare
Activate
Recover
Prepare
In the first step — prepare — patients complete short sessions of aerobic exercise intervals, typically on a stationary bike or treadmill. This triggers the release of a series of neurochemicals, including one called brain-derived neurotrophic factor (BDNF), which boosts the effect of subsequent therapy. Crucially, BDNF is a key component in healthy memory function.
Activate
During the second step — activate — patients engage in various therapies, including occupational therapy, neuromuscular therapy, neurointegration therapy, cognitive therapy, sensorimotor therapy, vision therapy, vestibular therapy, and others. While most of our patients receive many of the same types of therapy, each patient will receive exercises and combinations of therapies that are closely tailored to that person’s brain injury and evaluation results.
Recover
The final step — recover — involves periods of rest and relaxation in between therapy sessions. This may include breathing exercises to promote relaxation, neuromuscular massage of the neck and shoulders, and mindfulness exercises.
This treatment cycle aims to restore healthier neurovascular coupling, improve ANS function, and reduce the incidence and severity of PCS symptoms, including memory problems.
One of the main therapies for patients struggling with memory is cognitive therapy. Therapists will ask patients to complete a series of exercises that promote thinking, concentration, and memory. For example, working on short-term memory may involve reading a short text and then answering a few simple questions to see how much information you can retain. Or, you might be asked to memorize a series of photographs and recall details at your appointment the following day.
Given its connection with memory, therapy also involves exercises to improve your attention. For example, a game for selective attention (the ability to focus on only one thing) involves tapping whenever you hear a pair of opposite words in a list (such as ‘room’ ‘hot’ ‘cold’ ‘bear’ ‘door’), while ignoring the news radio playing in the background.
Our therapists can also improve your divided attention (the ability to switch between tasks) by asking you to sort cards by suit with the cards facing down at the same time as doing simple math calculations.
Once treatment is completed, patients meet with a member of our team to assess progress and to assign an at-home routine. The list typically includes a few aerobic exercises, cognitive activities, and ways to rest. Doing these exercises at home is a good way to ensure long-term recovery after treatment.
Strategies to Help with Memory Loss After a Concussion
PCS patients often struggle to remember things from day to day. Here we describe a few different strategies to use at home to help patients cope with memory impairments during their recovery.
Enhancing memory and attention with targeted exercises can significantly improve memory function in PCS patients. These exercises are only effective if you do them consistently. Gradually increase the duration and complexity of these exercises to improve your cognitive skills.
A few examples include:
Attention Shifting & Alternating Attention: Patients need to engage in a physical task combined with a cognitive task. For example, while doing housework, start a conversation with a family member. This exercise helps your brain switch between different tasks, supporting cognitive flexibility and multitasking skills.
Selective Attention: Patients need to perform a task while intentionally incorporating distractions. For example, patients may try to do simple work while listening to music or a podcast. Distractions need to be noticeable but not overwhelming. This exercise aims to help patients filter out irrelevant stimuli while maintaining concentration on the task they need to complete.
Sustained Attention: Patients need to choose an activity that requires their complete attention, such as reading a book or practicing a musical instrument. Start with short periods of attention and gradually increase the time spent on the task. This exercise aims to help patients improve their ability to stay focused on a single task for a prolonged period.
Encoding Strategies
Patients can improve memory recall by using a variety of memory encoding strategies. Using these methods on a regular basis can enhance the way your brain encodes and stores memories, making them easier to retrieve later on.
A few examples include:
Write it down: Writing down your thoughts can help with memory retrieval. Actually writing on paper with a pen is more effective than typing.
Create stories: Develop imaginative stories to interconnect your memories and improve recall.
Use categorization: Grouping elements that are similar aids in memory consolidation.
Use mnemonic tools: Using acronyms, songs, and rhymes can significantly augment memory. This form of association is one of the best ways for your brain to learn new information.
Explain it to others: Explaining new information to others helps improve memory retention.
Use visualization: Creating vivid mental snapshots of objects and their locations improves memory recall. Usually, the crazier the image, the easier it will be to remember.
Use repetition: Repeating information multiple times enhances memory.
Chunk information: Breaking down information — like phone numbers — into manageable segments helps with memorization.
Use associative techniques: Establishing connections between new information and pre-existing knowledge improves memory recall.
Compensatory Memory Strategies
In addition to attention and memory exercises and encoding strategies, PCS patients may also benefit from using multiple compensatory strategies to provide additional support for memory retention.
A few examples include:
Use a daily planner: Use a calendar to organize your tasks, appointments, and commitments. You need to update it regularly to ensure that important information is readily available, reducing the chances of forgetting crucial events.
Plan your week: Plan important upcoming activities and responsibilities for the following week. Visualizing the week ahead can help you allocate time more effectively and give specific slots for memory-intensive tasks.
Create checklists for cleaning: Create a checklist for cleaning each room of your house. This method ensures that you don’t overlook any cleaning tasks and gives you a visual guide.
Create morning and evening routines: Write down morning and evening routine checklists. These step-by-step lists help you during the day and free up cognitive resources for other tasks.
Create an exit checklist: Put an exit checklist on your door listing all the items you need before leaving the house, such as keys, wallet, and phone. This practice reduces the chances of leaving essential items behind and eliminates last-minute stress.
Create a checklist of bills: To make sure you never miss a payment, create a list of all outgoing bills you have each month and the date on which they are due.
Keep an exit box: Keep a box near your door where you store the items you need before leaving the house. Always store these items, such as keys or glasses, in the same box so that they’re always easy to find.
Lifestyle Choices
Combined with therapy and compensatory strategies, these lifestyle changes can help PCS patients recover faster and overcome their memory issues. A few examples include:
Engage in regular physical activity: In addition to improving fitness and strength, regular exercise can also help with memory function. Exercise also indirectly boosts memory and attention by improving mood and sleep and reducing stress and anxiety.
Stay mentally active: Keeping the brain active can help patients recover their cognitive skills, including memory and attention. Anything from learning to play a new musical instrument to playing board games with friends and family can help.
Keep an active social life: Social interaction helps ward off feelings of isolation and depression, which aggravate memory problems. Look for opportunities to get together with friends and family, go out for a meal, or volunteer at a local charity.
Follow a healthy sleep pattern: Not getting enough sleep can affect your memory. Try to go to bed and get up every day at the same time, avoid caffeinated drinks and alcohol in the evening, and engage in something relaxing before going to bed.
Eat a healthy and memory-boosting diet: A healthy and balanced diet is good for your brain and protects cognitive skills, including memory. Eat plenty of fruits, vegetables, and whole grains; avoid highly processed sugary or fatty items. Limit alcohol consumption.
Memory problems after a head injury are more common than most people realize. They can happen after even a mild brain injury with no loss of consciousness. Fortunately, there are treatment options for this long-term symptom of head injury. If you want to learn even more about memory problems after head trauma, see our post on memory loss recovery stories & FAQs.
If you’re experiencing symptoms that won’t resolve after a mild traumatic brain injury, you’re not alone. And you’re not crazy. 90% of our patients show symptom improvement after just one week of treatment at our center specializing in post-concussion therapy. To see if you are eligible for treatment, sign up for a consultation.
Dr. Mark D. Allen holds a Ph.D. in Cognitive Science from Johns Hopkins University and received post-doctoral training in Cognitive Neuroscience and Functional Neuroimaging at the University of Washington. As a co-founder of Cognitive Fx, he played a pivotal role in establishing the unique and exceptional treatment approach. Dr. Allen is renowned for his pioneering work in adapting fMRI for clinical use. His contributions encompass neuroimaging biomarkers development for post-concussion diagnosis and innovative research into the pathophysiology of chronic post-concussion symptoms. He’s conducted over 10,000 individualized fMRI patient assessments and crafted a high-intensity interval training program for neuronal and cerebrovascular recovery. Dr. Allen has also co-engineered a machine learning-based neuroanatomical discovery tool and advanced fMRI analysis techniques, ensuring more reliable analysis for concussion patients.
Risk of Parkinson’s more than double for people with anxiety
25 June 2024
The risk of developing Parkinson’s is at least twice as high in people with anxiety compared to those without, finds a new study by UCL researchers.
The research, published in the British Journal of General Practice, investigated whether there was a link between people over the age of 50 who had recently developed anxiety and a later diagnosis of Parkinson’s.
The team, led by Professor Anette Schrag at the UCL Queen Square Institute of Neurology, used UK primary care data between 2008 and 2018 and assessed 109,435 patients who had developed anxiety after the age of 50 and compared them to 878,256 matched controls who did not have anxiety.
They then tracked the presence of Parkinson’s features – such as sleep problems, depression, tremor and balance impairment – from the point of their anxiety diagnosis up until one year before the date of a Parkinson’s diagnosis, to help them understand each group’s risk of developing Parkinson’s over time and what their risk factors might be.
The team made sure to adjust the results to account for age, sex, social deprivation, lifestyle factors, severe mental illness, head trauma and dementia – which may affect the likelihood of developing the condition in people with anxiety.
Consequently, they found that the risk of developing Parkinson’s increased two-fold in people with anxiety, compared to the control group.
They also confirmed that symptoms such as depression, sleep disturbance, fatigue, cognitive impairment, hypotension, tremor, rigidity, balance impairment, and constipation, were risk factors for developing Parkinson’s in people with anxiety.
Co-lead author, Dr Juan Bazo Alvarez (UCL Epidemiology & Health), said: “Parkinson’s disease is the second most common neurodegenerative condition worldwide, and it is estimated that it will affect 14.2 million people by 2040.
“Anxiety is known to be a feature of the early stages of Parkinson’s disease, but prior to our study, the prospective risk of Parkinson’s in those over the age of 50 with new-onset anxiety was unknown.
“By understanding that anxiety and the mentioned features are linked to a higher risk of developing Parkinson’s disease over the age of 50, we hope that we may be able to detect the condition earlier and help patients get the treatment they need.”
Parkinson’s disease is the world’s fastest growing neurodegenerative disorder and currently affects nearly 10 million people across the globe.
The condition is a progressive disorder that is caused by the death of nerve cells in the part of the brain called the substantia nigra, which controls movement. These nerve cells die or become impaired, losing the ability to produce an important chemical called dopamine, due to the build-up of a protein called alpha-synuclein.
A team of researchers, led by scientists at UCL and University Medical Centre Goettingen, Germany, have recently developed a simple blood test that uses artificial intelligence to predict Parkinson’s up to seven years before the onset of symptoms*.
Co-lead author Professor Anette Schrag (UCL Queen Square Institute of Neurology) said: “Anxiety is not as well researched as other early indicators of Parkinson’s disease. Further research should explore how the early occurrence of anxiety relates to other early symptoms and to the underlying progression of Parkinson’s in its early stages.
“This may lead to better treatment of the condition in its earliest stages.”
The researchers advise that future research should explore why people aged over 50 with new-onset anxiety are more at risk of Parkinson’s and whether their outcomes are affected by the severity of anxiety.
This study was funded by the European Union AND-PD grant.
A male ostrich providing shade to ostrich chicks on a hot day in Samburu National Reserve in Northern Kenya 🇰🇪
Male ostriches are known to be really stellar dads and provide protection and care for their young ones from incubation and even after they hatch. pic.twitter.com/TWt8sVJcdk
Researchers studied the invisible dimension of household labor: the cognitive effort that goes into anticipating needs, planning, organizing, and delegating household tasks.
When you think about household chores, you likely think of actions: scrubbing the dishes, running errands, chopping vegetables for dinner. And it’s not news to say that mothers often shoulder the burden for most of those activities.
But there’s an invisible dimension of household chores that unfolds behind the scenes: the cognitive effort that goes into anticipating needs, planning, organizing, and delegating household tasks. In other words, someone has to remember to replace the dish soap and select which vegetables to chop.
Our new research found that this cognitive dimension of household chores, often called the “mental load,” is divided even more unevenly within couples than the physical dimension—and it seems to take a particular mental health toll on women. According to the study we published in the Archives of Women’s Mental Health, mothers who take on a more disproportionate share of cognitive household labor report higher levels of depression, stress, relationship dissatisfaction, and burnout.
Tracking who does what
We asked 322 mothers of young children about who in their family is responsible for 30 common household tasks. We collaborated with the creators of the Fair Play system—a book and card game designed to better quantify the division of labor within households—to divide each task into two dimensions: cognitive (anticipating, planning, delegating, and thinking about household tasks) and physical (the hands-on execution of household tasks). We then examined how these tasks are shared between partners.
We found a striking gender disparity: Mothers not only performed more physical household chores, but also carried a significantly greater share of cognitive labor compared with their partners.
On average, mothers reported being responsible for about 73% of all cognitive household labor compared with their partners’ 27%, and 64% of all physical household labor compared with their partners’ 36%. Indeed, for every single task we examined, the gender difference was larger for the cognitive dimension than the physical execution dimension.
There was only one task in which fathers did more planning and execution: taking out the garbage. Fathers also carried out more home maintenance tasks, but mothers did more of the related planning.
Interestingly, while an unequal division of physical tasks was linked to worse couple relationship quality, it was the cognitive labor that had a more profound impact on women’s psychological well-being.
Our study is one of the first to investigate the cognitive dimension of household labor and its effects on maternal mental health. Cognitive labor may be particularly taxing for women because it often runs behind the scenes and goes unacknowledged or unappreciated by others. It also pulls mental energy away from other priorities.
Our study was limited by its reliance on self-reported household labor and by the fact that we were able to collect data only from mothers in cohabiting, heterosexual couple relationships. Future studies can survey both partners and directly observe what chores couples do at home. They can also look at different kinds of relationship configurations, including gay and lesbian couples.
We also don’t know much about the long-term effects of the division of cognitive labor on women’s mental health and cognitive functioning.
The unfair division of household chores is a frequent source of stress in relationships and is often cited by women as a reason for divorce. The cognitive load may be an underappreciated aspect of the domestic workload that warrants more attention from couples therapists, mental health counselors, and premarital relationship educators.
Apply to the Most Innovative Companies Awards and be recognized as an organization driving the world forward through innovation. Early-rate deadline: Friday, August 23.
Work Smarter, not harder. Get our editors’ tips and stories delivered weekly.
In January 2021, Maeve Boothby O’Neill took stock and summed up her position. “I’ve been tired since I was 13,” she wrote. “When I was 18, I was diagnosed with ME/CFS. I hoped I would finally get treatment and recover my health. I had every potential to be an asset to humanity and hoped and intended to advance the cause of human flourishing.”
Maeve, a bright, diligent, determined young woman, and her loved ones did their best over the years to get help but the treatment – and the fundamental understanding of myalgic encephalomyelitis/chronic fatigue syndrome – just was not available.
She wrote: “I cannot adequately describe how frightening it is to discover there are no doctors who can help you, they do not even know what is wrong with you. I am fighting for a chance to live.”
By March 2021, her ME was so severe that she was unable to sit up, hold a cup to her lips or chew. She was admitted to hospital, desperate to find a way of taking on food and drink. Despite the pain she was in, she clearly still wanted to live but, in the end, was hardly able to move, communicate or tolerate light, sound or touch – not even a loving hug. She died at home in a garden flat in Exeter on 3 October 2021, at the age of 27.
On Friday, Deborah Archer, the assistant coroner for Exeter, Plymouth, South Devon and Torbay, concluded that Maeve had died from natural causes “because of severe myalgic encephalomyelitis (ME)”.
During the harrowing two-week inquest, her parents, Sarah Boothby and Sean O’Neill, described their increasingly desperate efforts to find help for her from doctors and their desire to try to improve treatment for people in her position, keenly watched by ME campaigners and patients with the illness.
Maeve Boothby O’Neill had dreamed of travelling after school
The hope is that her story will come to be seen as a landmark case that will lead to change in the way people with ME are treated and perceived.
Everyone agrees Maeve was an exceptional person. She was a vivacious child, a brilliant student and linguist with a deep interest in world affairs who dreamed of travelling after school.
As a young girl, she was robust and energetic. It is not clear what caused her ME but her tiredness began after she and her mother caught a mild virus when Maeve was 12.
Her father, in his statement to the inquest, said: “I remember picking her up one day from South Dartmoor college in a state of some distress; she had become dizzy and fainted while cross-country running.”
It was hard to find what was wrong. A paediatrician told Maeve her symptoms were “all in her mind”. She once asked her mother: “Do you think I’m making it up?”
Despite her persistent tiredness, she did well at school and had offers for Russell Group universities. In 2011 she was finally diagnosed at a Bristol hospital as having ME. She was unable to take up a place at university and over the next 10 years steadily declined.
She was determined to be a good patient and found out everything she could about ME. But, her father said: “Medicine and medics did not know what to do. Maeve encountered treatments that made her worse, such as exercise programmes, delayed diagnoses, ignorance, apathy and stigma.
“The medical orthodoxy is that ME is a behavioural problem or a psychological illness and that belief is deeply rooted in the NHS despite growing scientific evidence that it is a physical illness.”
During the inquest, Dr David Strain, an honorary consultant at the Royal Devon and Exeter foundation trust, who was involved in Maeve’s treatment, said the disease had been stigmatised because it did not have a diagnostic test.
He said: “Even today there are people who have been through the historic medical schools that didn’t recognise this as a physical disease. That’s a travesty.”
Strain also said there was nowhere to treat people with ME. “I don’t think there is a ward anywhere in the country that is appropriate to manage ME patients,” he said.
Maeve became increasingly housebound, isolated and unable to take care of herself. Her mother had to give up her career to help her.
Maeve had begun writing a series of novels set on Dartmoor, where she had grown up
Yet Maeve was still ambitious.She began writing a series of novels set on Dartmoor, where she had grown up. She seemed to draw on her experiences to describe the loneliness of one of her characters, a bereaved woman: “The great grief she carried for the irretrievable loss of others but also of her former self was a wound that could not heal.”
By March 2021, it was becoming very difficult for her to eat or drink and she told her mother: “I need someone to know how unwell I am.” She was taken to the Royal Devon and Exeter hospital (RDH) but discharged the same day.
Her father was in hospital at the same time, being treated for cancer. He said: “It seems a harsh thing to say but she would have been better off in the hands of the NHS if she had had cancer.
“She and I were both in hospital around the same time. I was having state-of-the-art keyhole surgery. My treatment was swift, skilful and effective. Maeve presented as acutely ill – immobile, weak, in pain and unable to digest food and in danger of malnutrition – only to be told there was nothing that could be done for her. Within hours of her admission, she was bundled back into an ambulance and sent home.
“In my view, it was deeply discriminatory. Had Maeve presented with those symptoms but with a diagnosis other than ME, I believe she would have been treated very differently.”
In June 2021 Maeve wrote to her GP, Dr Lucy Shenton: “I really need help with feeding. I am hungry. I want to eat. I have been unable to sit up or chew since March. Please help me get enough food to live.”
Shenton, who worked hard for Maeve, was not well enough to give evidence to the inquest in person because she had suffered post-traumatic stress disorder over the case. But in a statement read out in court, Shenton summed up the issues neatly: “There needs to be more funding and research into ME to provide the evidence and guidelines for clinicians to work from.
“There needs to be somewhere in the NHS that provides specialist care for patients with severe ME and an easy mechanism to access that provision. There needs to be a way for the patient’s voice to be heard in meetings. Clear systems with appropriate safety nets ought to be in place.”
Maeve was admitted to hospital twice but attempts to help her to eat and drink failed. “Maeve was starving to death,” her mother said. It wasn’t that she did not want to eat. “She had a good appetite. She was hungry all the time, enviously asking me what I would be eating, and making menu suggestions for meals she would have eaten if she could.”
Maeve made it clear she wanted to be discharged from hospital. Her mother said: “If she had to die from starvation with severe ME, she wanted it to be in the familiarity of home and the care of those she loved.”
O’Neill told the inquest it had been difficult to get his daughter the palliative care she needed as she became critically ill because there was still suspicion that her illness was invented. Boothby said she died “in the company of those she loved”.
Maeve Boothby O’Neill ‘encountered treatments that made her worse’, said her father
Sonya Chowdhury, the chief executive of Action for ME, said she hoped Maeve’s case would prompt change. She said: “It is clear that the NHS has not yet developed the framework to deliver effective support to people with severe and very severe ME.
“There is no clear pathway for care and this is compounded by a lack of understanding that some healthcare professionals have and, as we have seen in situations like Maeve’s, stigma. There is no excuse for this.
“The scientific understanding for ME is lacking as a result of major underinvestment in research over the years but that is no excuse for what we have heard in Maeve’s situation.
“The overarching theme emerging is the absence of anyone with knowledge of ME and the reluctance of anyone to take responsibility. It would be too easy to blame any one individual; this is a system-wide problem and one that the NHS has responsibility to take leadership of to prevent further harm.”
Action for ME is calling for the government to release a delivery plan on ME/CFS initially promised by the Conservative government in 2022 but delayed multiple times.
Chowdhury called for more research funding. She said: “We would like the government to urgently accelerate strategic investment in ME research to ensure it achieves a commensurate level with other disease areas and identify treatments.
“There is a clear and unmistakable stigma around ME that stems from a lack of understanding. Still so little is known about this disease and its causes and we desperately need to see more research commissioned to address this.”
She said there needed to be “proper implementation” of the Nice guideline for ME/CFS, including the inclusion of ME in training.
The last words should go to Maeve. In her January 2021 statement she wrote: “My only hope lies in biomedical research, and adequate funding for this requires the medical establishment to set aside the inaccurate idea that behavioural treatments can cure ME.” She added: “This is not political, it is existential.”
From hermaphroditic wood carvings to stacks of 250,000 papers, a collection showcases the greatest artistic works by German psychiatric patients.
At the start of the 20th century, doctors thought they could use patients’ paintings to diagnose their psychiatric conditions. This turned out to be largely untrue, but, even so, painting remains an important part of psychiatric treatment to this day. The act of painting allows patients to come to terms with traumatic experiences, fears and their experiences of illnesses — and sometimes the results are remarkable pieces of art.
As early as the 1920s, art historian and junior doctor Hans Prinzhorn recognized the talent in his patients at the Heidelberg Psychiatric Clinic, and began collecting their works. The world-renowned Prinzhorn Collection at Heidelberg’s University Hospital now contains over 5,000 drawings, oil paintings, wood carvings and textile works.
“Art allows patients to release their inner tension,” says psychotherapist and art historian Georg Franzen, director of the Institute for Art Psychology in Celle. A hundred years after Hans Prinzhorn began his collection, art has become an integral part of psychiatric care: Today, almost all clinics offer art therapy in addition to psychotherapy and medication.
A Growing Phenomenon “Patients are able to express inner pictures with a brush and a pencil in a way they wouldn’t be able to with words,” Franzen continues. The works serve as a starting point for conversations between therapists and patients, as they discuss the color and form of the feelings and thoughts they’ve put to paper. Franzen explains, “Creative work improves patients’ concentration, emotional competence and feeling of self-worth.”
It’s not unusual for former psychiatric patients to establish a living for themselves as artists. So-called “outsider art” is a now a permanent fixture on the art market, and even if illness is often is the driving force behind the artists’ work, it can then take a backseat to their creativity.
These days, open workshops used by artists with mental health issues are attracting ever more notice. “Art colleges visit them regularly to experience their unique, creative atmosphere,” says psychologist and art historian Thomas Röske, director of the Prinzhorn Collection since 2002. Since 1980, a further 12,000 works by patients past and present have been brought into the collection, which continues to grow.
Jana Hauschild is a psychologist and works as a freelance journalist in Berlin.